Six steps between a search and a booked patient.
A self-pay patient walks the same path every time. Each step is a place they can quietly drop out, and each one has a fix. The rest of this page takes them in turn.
- 1 They search nothing specific to find
- 2 They read your page no fee, no “how soon”
- 3 They look you up details that don’t match
- 4 They get in touch it’s 22:40
- 5 Someone calls back it waits in the inbox
- 6 They leave a review nobody asked
Start with one enquiry.
Here is a test you can run this week. Take the last self-pay enquiry your practice received and ask your secretary four questions. Wherever the trail goes cold is where to start, and it's usually one or two places, not ten.

- Where did it come from? Google, then the website form
- How long before someone replied? Thursday afternoon
- Was a consultation booked, and did they attend? Nobody knows
- If not, does anyone know why? Nobody knows
The trail goes cold here. Start looking here.
The demand is there. Booking is the hard part.
Plenty of people are willing to pay privately, and they choose carefully. The practices that make choosing easy are the ones that get chosen.
Private inpatient and day-case admissions in 2025, a record for the fourth year running.
282,625 self-pay, roughly three in ten
PHIN, June 2026 market updateSelf-pay share of admissions in Q1 2026, the most self-pay admissions PHIN has recorded in a quarter, up 7.7% on the year.
Mainly cataract surgery and patients over 60. PHIN says it is too early to call a trend.
PHIN, September 2026 market updateGrowth in self-pay revenue in 2024. Plenty of people will pay; the spending is not growing, so they choose carefully.
LaingBuisson, 2024 market reportIf you want to work out what a few more self-pay patients would mean for you, our guide to getting more private patients starts there.
Being found, in search and AI.
YouGov's July 2026 survey found search engines are still the first stop for health information (26%), with 8% going first to AI tools. That's health information in general rather than choosing a consultant, but it's where some patients now start.
Google's own position is reassuring. Its AI Overviews and AI Mode build on core Search with “no additional requirements”, and its May 2026 guidance says optimising for generative AI is “still SEO”. For ChatGPT, OpenAI says sites that block its OAI-SearchBot crawler won't appear in ChatGPT search answers, though they may still show up as plain links.
- What you control
- A specific page for each condition and procedureWritten from your own practice
- Profiles that agree with each otherWebsite, hospital, PHIN, directories
- An accurate Google Business ProfileHours, location, phone, reviews
- Where patients read answers
- Google SearchThe first stop for 26% of UK adults looking for health information
- Google AI Overviews and AI ModeBuilt on core Search. No extra requirements.
- ChatGPT searchOnly if OAI-SearchBot isn't blocked
What a self-pay patient needs to see before booking.
PHIN's 2024 research on patient priorities found that cost and payment options were the factor most often named when choosing a consultant, by nearly half of respondents, and that 71% were going private at least partly because of NHS waits or treatment being unavailable. PHIN's 2026 patient confidence report found self-funders want more help to decide than insured patients do: 29% said they'd find it easy to decide without trusted information, against 44% of insured patients.
That is good news for you. Self-funders are looking for exactly the information you already have.
- 1Can I trust them?Training, GMC number, where they practise
- 2What will it cost?A guide fee that matches PHIN, with what it includes
- 3Can I pay myself, or use insurance?Both, and which insurers recognise them
Mr A. Example FRCS (Orth)
Consultant hand and wrist surgeon
1GMC 0000000 · Fellowship, hand surgery
Includes hospital, surgeon and anaesthetist. Excludes scans. Matches PHIN.
5No GP referral needed to pay yourself
Answered 8:30–18:00. Out of hours, we call you back first thing.
- 4How soon?A typical wait, dated, not promised
- 5Do I need a referral?A straight answer
- 6How do I book?One tap, the hours it's answered, what happens next
Who you are, in plain facts
Your training, GMC number, the procedures you perform, the hospitals where you hold practising privileges, and the days you consult at each. “Fellowship in hand surgery, Oxford” tells a patient more than “leading hand surgeon”, and it's a claim you can stand behind.
What it costs
Your fees are probably public already. The CMA's 2014 Private Healthcare Order requires consultants to give PHIN their consultation and standard procedure fees and keep them up to date. By October 2025 the CMA reported that 96% of consultants publish self-pay consultation fees on PHIN, and in July 2026 it confirmed full compliance.
The Order also says that once an outpatient appointment is confirmed, the patient gets an estimated cost (a range is fine if you explain what changes it), any financial interests, the insurers that recognise you, and PHIN's web address. We haven't found a rule requiring fees on your own website, so a guide fee there simply brings forward what the patient will receive anyway. The GMC's conflicts-of-interest guidance (paras 26–28) asks you to be open about fees before treatment. A good guide fee says what's included (hospital stay, follow-ups, whether the anaesthetist's fee is in) and what isn't (diagnostics, further tests), and matches PHIN.
“Can I be seen privately, and how soon?”
Your secretary probably answers this more than anything else. The page should answer it too: self-pay, insured or both; which insurers recognise you; whether a GP referral is needed; and the current typical wait for a new appointment, dated, as a guide rather than a promise.
How to book
Try your own booking route on your phone, in the evening when the office is closed. There should be one obvious way in, a number you can tap, the hours it's answered, and a line saying what happens next.
What a bookable self-pay page answers
Ten questions, in the four things a patient is trying to settle.
Is this the right person?
Is this the right specialist for me?
The conditions and procedures you treat, in plain language
Can I trust them?
Training, GMC number, hospitals with privileges, verifiable experience
What do other patients say?
Genuine reviews, shown in full or linked
What will it cost me?
What will it cost?
Consultation fee and guide procedure fees matching PHIN, with what's included and what isn't
Can I pay myself, or use insurance?
Self-pay and insured, and the insurers that recognise you
Do I need a referral?
Yes, no, or “depends on your insurer”
When and where?
How soon?
Typical current wait, dated, never promised
Where?
Each location, your clinic days, parking or transport
What happens next?
What are the risks and recovery like?
An honest summary, with nothing played down
How do I book?
One route, its hours, and a response time you can keep
Referred patients search your name before they book.
GPs are the most trusted source when people choose private care: PHIN's 2026 report puts them at 53%, with word of mouth at 35%. A referral is a strong start, and the patient will still look you up, often the same evening.

example-practice.co.uk
Mr A. Example · Hand and wrist surgeon
Clinics on Thursdaysaat The Example Hospital. Fees: please contact usb.
The Example Hospital › consultants
Mr A. Example, Consultant Orthopaedic Surgeon
Outpatient clinics: Tuesdaysa, 9am to 1pm.
phin.org.uk › consultant
Mr A. Example · Private Healthcare Information Network
Initial consultation fee: £000b. Recognised by most major insurers.
Review site › hand surgeons
Mr A. Example reviews
★★★★★ 4 reviews · most recent 2021c
- aWhich day? The hospital says Tuesday. The website says Thursday.
- bWhich fee? PHIN shows one. The website says to ask.
- cStill practising? The newest review is years old.
- Nothing here is dramatic. The patient is just left unsure which details to believe.
The only hard number here is American: a 2021 US consumer survey by Press Ganey found 83% of people read reviews of a provider they'd been referred to. Whatever the UK figure, making sure what they find is right costs very little.
Where enquiries stall: after hours and in the inbox.
If a patient enquires after your office has closed, what happens next? An automatic acknowledgement should explain when to expect a reply, and someone should be responsible for following up the next working morning.
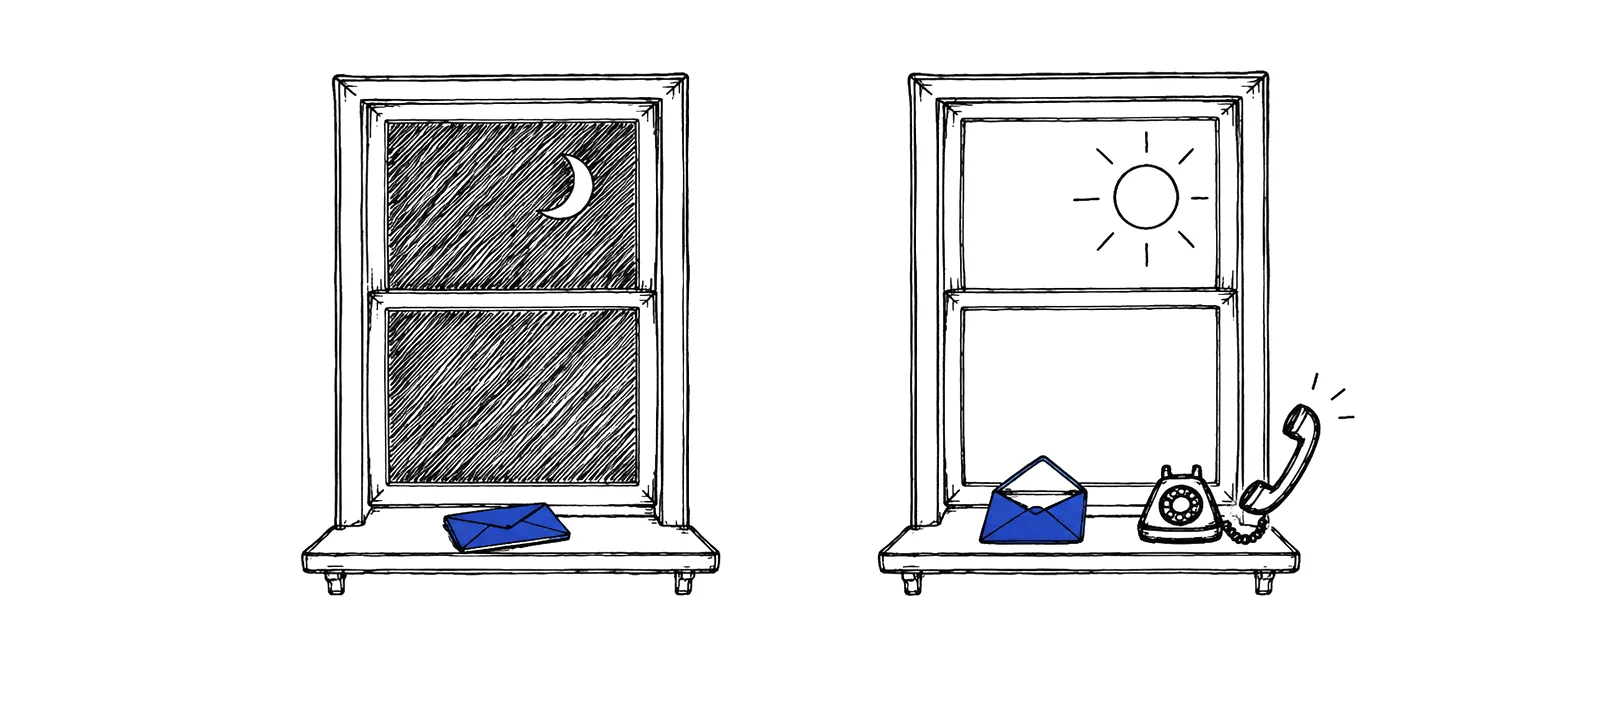
Without a routine
- Tue 22:40 Form lands in a shared inbox
- Wed 08:30 Nobody has looked yet
- Wed, all day Secretary is at the hospital all day
- Thu 15:10 Reply sent. If they've booked elsewhere, nobody will know.
With the routine
- Tue 22:40 Acknowledged at once: who will call, and when
- Wed 08:30 Called back first thing, with the enquiry and its source to hand
- Wed, all day Secretary is at the hospital. Nothing is waiting.
Reviews: collect properly, show honestly.
In PHIN's 2026 report, only 7% of people counted review websites among the sources they'd trust. Yet in its 2024 research, reviews and recommendations were picked almost as often as qualifications when choosing a consultant. People may not trust reviews on their own, but they look at them. Many practices simply never ask, so a steady trickle of recent reviews stands out.
- Care finishes Discharge or final follow-up
- One request Same words, every patient
- One polite reminder Then nothing more
- A review, or not Shown as it comes
Never, under the DMCC Act 2024
- Pressure to leave one
- A thank-you gift in return
- Hiding the bad ones
Since 6 April 2025 the Digital Markets, Competition and Consumers Act 2024 has banned fake reviews, concealed incentives and misleading display such as hiding negative reviews. Testimonials on your own site should be genuine, consented and about the patient's experience, and the selection shouldn't give a misleading picture. The ASA is clear that a testimonial can't support a claim you couldn't make yourself.
Compliance is part of a good page.
The GMC holds you personally responsible for information published in your name. Good Medical Practice 2024 (paras 88–91) asks for it to be honest and accurate, without leaving out or playing down risk. Your website also falls under the ASA's CAP Code, so factual claims need evidence and prescription-only medicines can't be advertised to the public.
If you practise in England and consult remotely, including by video, the CQC's exception for doctors with practising privileges doesn't cover those consultations, and it excludes certain procedures too. The CQC covers England only. Check your arrangement with your defence body or the regulator's guidance.
None of this works against bookings. A patient who can see the fee, the risks and the recovery before getting in touch arrives ready for a proper conversation.
Before any page goes live
- Facts a patient can check, nothing left outGMC Good Medical Practice 2024, paras 88–91
- Risks and recovery stated plainly, nothing played downGMC Good Medical Practice 2024
- Every factual claim backed by evidence; no testimonial standing in for itASA / CAP Code
- No prescription-only medicines advertisedCAP Code 12.12
- Guide fees as you set them, consistent with PHINCMA Order 2014; GMC conflicts guidance
- The enquiry form asks for the minimum; no health data reaches ad toolsUK GDPR, ICO guidance
How Specialist Scale puts the whole path right.
Most consultants who've tried marketing have hired it in pieces: one firm for the website, another for search, someone for ads, and the secretary left holding the enquiries. Each supplier reports on its own slice, and nobody owns the gaps between them. That's where patients go missing, and it's why marketing split across separate suppliers tends to leak patients.
Hired in pieces
- Web agency reports form submissions
- SEO contractor reports rankings
- Ads agency reports cost per click
- Reviews tool reports star average
- Your secretary reports an inbox
One team
We take the opposite approach. One team builds and runs the whole path, month after month: how patients find you, the page they land on, how their enquiry is handled, the follow-up, and the review afterwards.
You get one monthly report, short enough to read between two patients. It opens with a plain answer to “is it working?”, then shows how people found you, the calls, forms and emails that came in by source, your local search visibility, the reviews requested and received, what we did that month, what's next, and anything we need from you, which is usually nothing.
Is it working?
Yes. More people found you through local search this month, and more of them got in touch.
Enquiries by source 29
- Website forms 12
- Calls from your Google listing 8
- Calls from the website 5
- Emails 4
Reviews
6 new
from 22 requests
Local search
6 of 9 areas
in the top three for your main search
What we did
Rebuilt the carpal tunnel page around the fee and the wait. Brought the hospital profile into line.
What's next
A page for trigger finger. Ask Google to index the new pages.
What needs you
Nothing this month.
Your secretary's diary shows which of those enquiries became consultations. Set that against what a private patient is worth to your practice and you can see what the work is returning. Alongside the report there's a quarterly check-in and an annual review. There are no weekly meetings and no status calls.
That's the standard good marketing for medical specialists should meet, whoever you work with. We take on a small number of consultants at a time, and you can see how live engagements run. New pages take months to reach their full effect, and we'll show you the progress every month rather than promise a number.